
Facial fat grafting in Beirut
Facial fat grafting uses a patient's own fat to restore volume and improve facial contours. I use it selectively, often in the temples, cheeks, brow, tear trough and around the mouth, either as a standalone procedure or alongside facelift, blepharoplasty and other facial surgery. The aim is not simply to add volume. Fat should be placed according to facial anatomy, in specific compartments and tissue planes, to restore proportion and soften transitions without making the face look fuller or heavier.
Facial aging is not simply volume loss
The face does not age simply because it loses fat. Aging involves changes in the skin, retaining ligaments, facial fat compartments and underlying skeleton, together with descent and redistribution of soft tissues. This distinction matters because adding volume cannot correct every sign of facial aging. A descended cheek or jowl, for example, should not simply be inflated with more volume. When true volume deficiency is present, however, carefully placed fat can restore contours and transitions that have become depleted with time.
Facial fat is organized into anatomically distinct superficial and deep compartments. I therefore graft fat selectively rather than treating the face as a single space. Depending on the anatomy, this may include the deep medial cheek, SOOF, temples, brow, chin, prejowl region and periorbital area.
Transferred fat is not than just a permanent natural filler
Fat grafting appears to do more than simply restore volume. Fat contains adipose-derived stem and stromal cells, and human studies have demonstrated increased collagen formation, elastic fibres and vascularity in the skin following fat grafting. These changes may contribute to the improvement in skin quality that is often observed clinically.
Transferred fat that survives becomes living tissue. Not all injected fat survives, and some resorption is expected during the first months. Long-term retention varies according to the recipient area, technique and individual patient factors. Once established, the surviving fat behaves like normal living fat and can change with significant weight gain or loss. Fat grafting is therefore long-lasting, but it is not predictable to the millimeter and occasional refinement may be necessary.
Cost-effective as one or two sessions can get you the result you need.
Same color hue and feel as normal skin.
Lower risk of allergy compared to fillers.
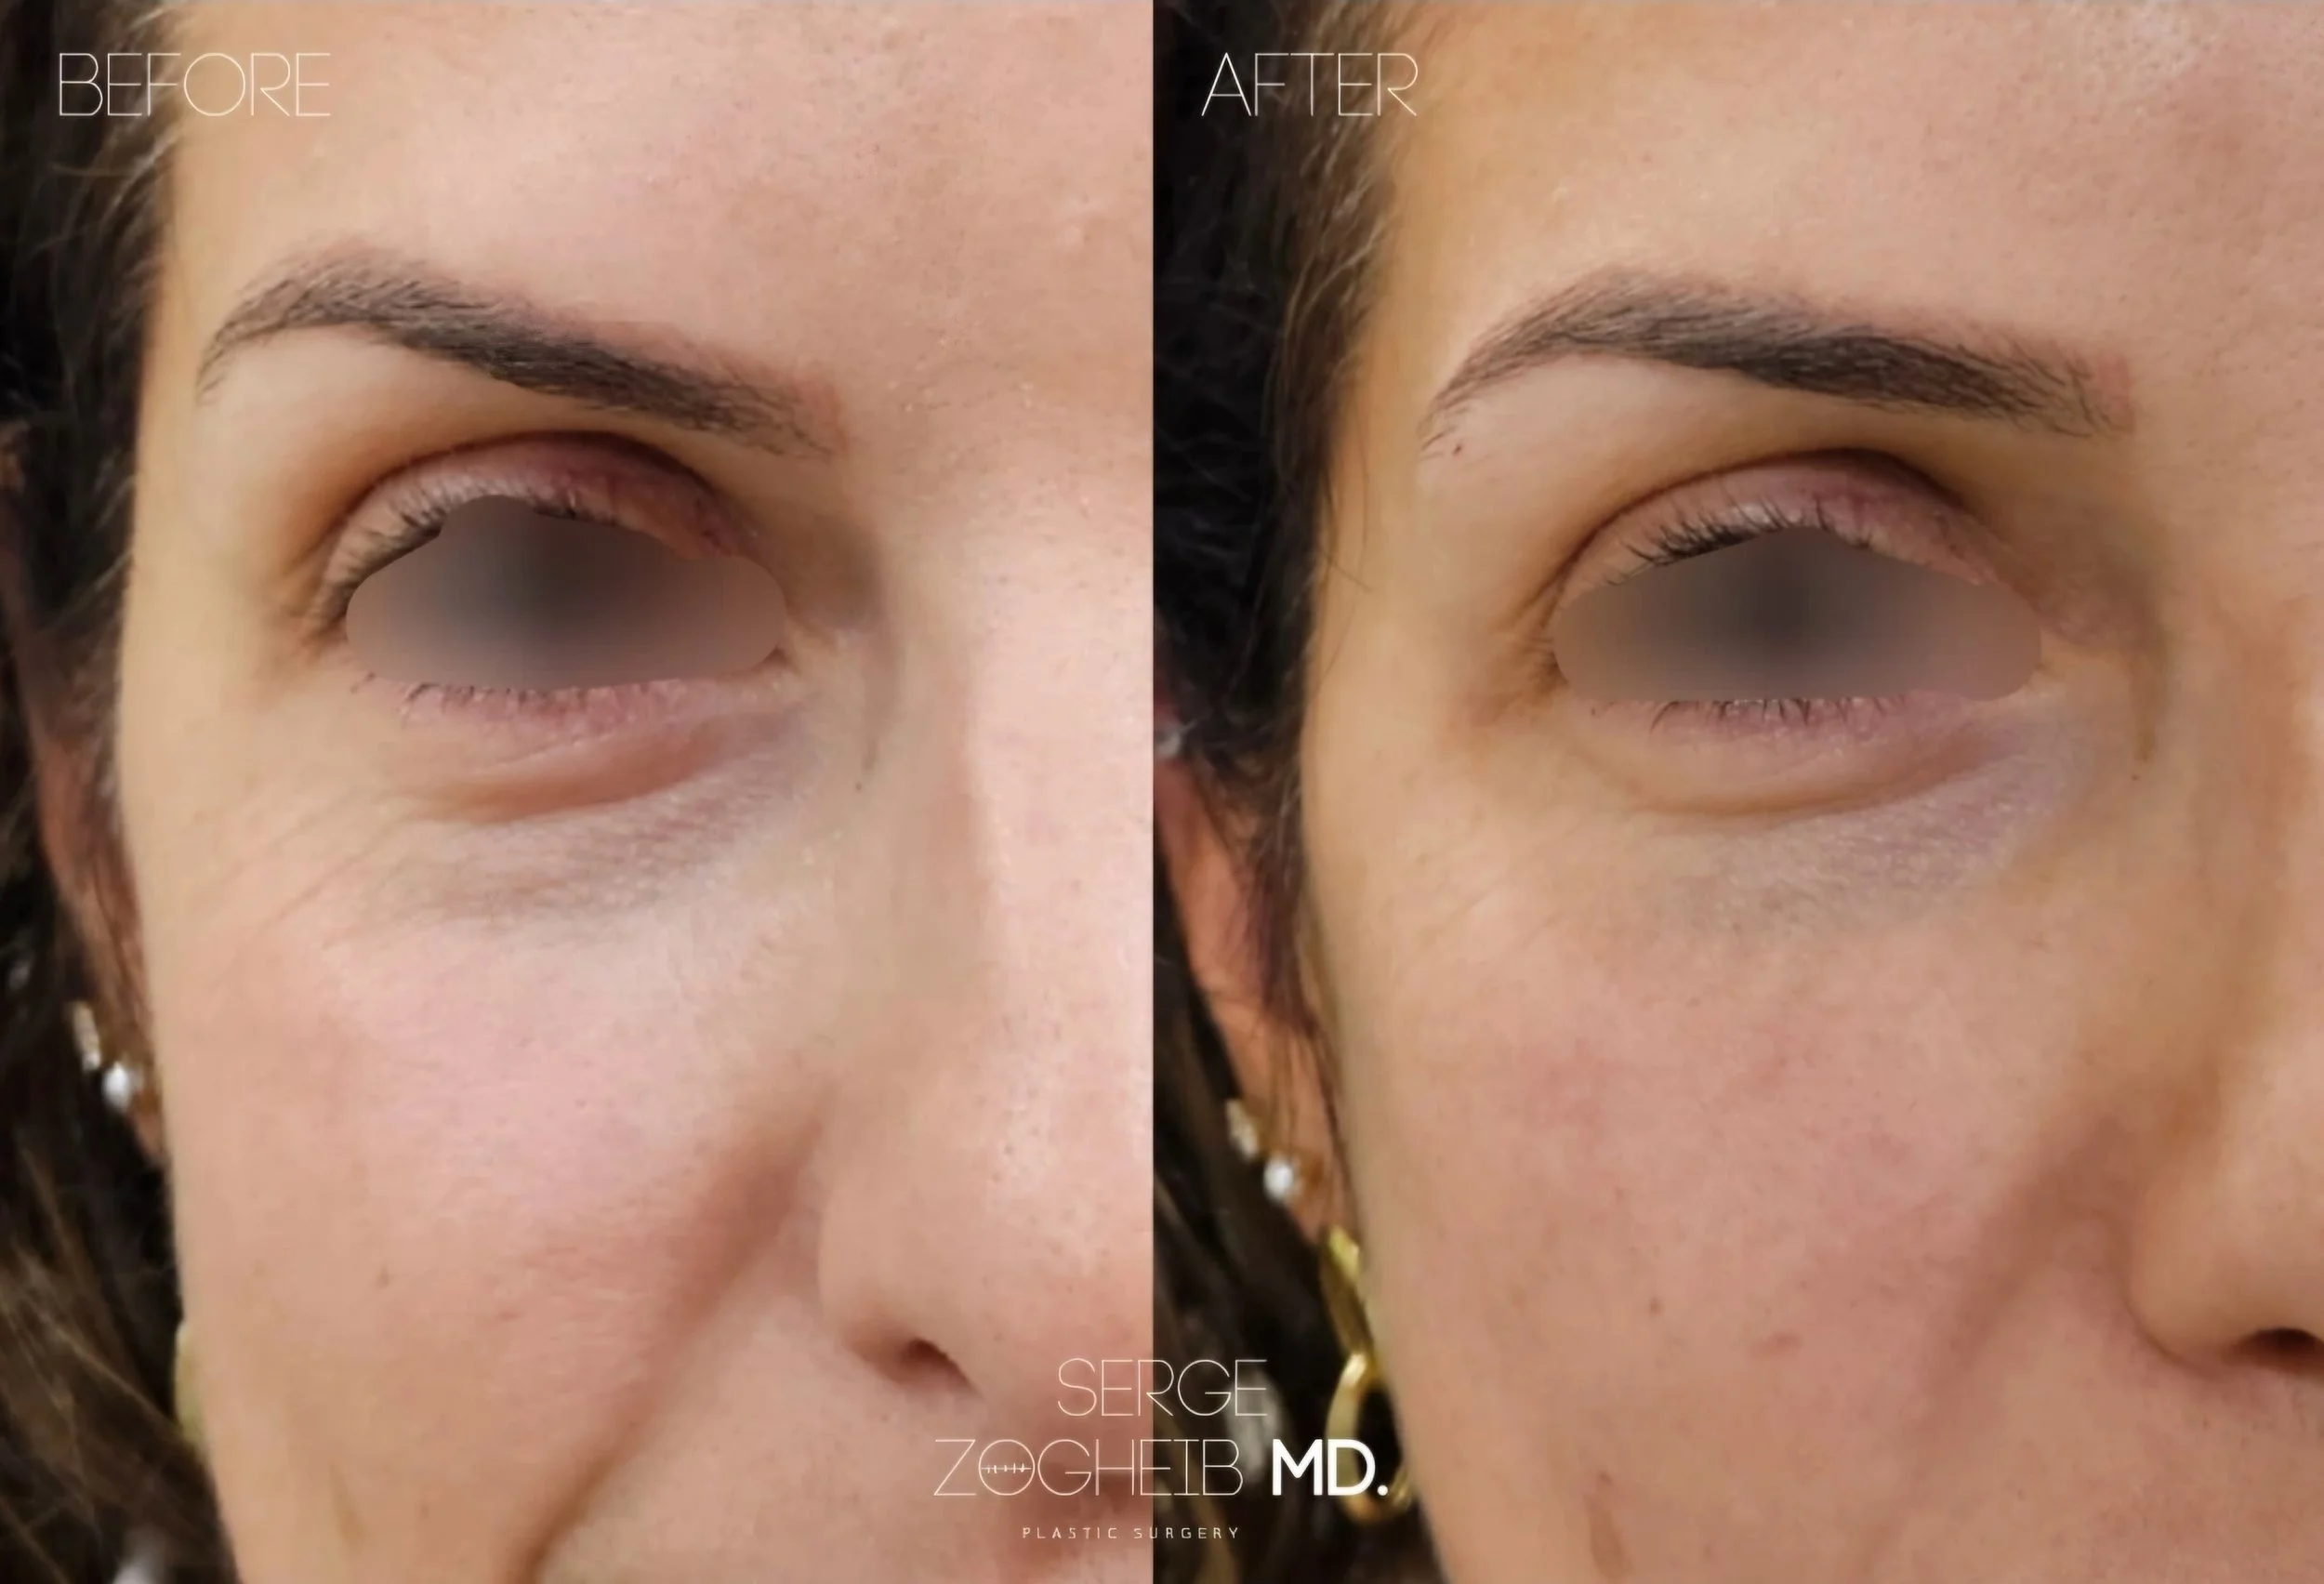
Fat grafting done to the deep medial cheek fat pad and SOOF. (Patient at 3 months post-operatively). Microfat grafting works exceptionally well in the under-eye region.
Where can facial fat grafting be used?
Upper eyelid, temples and brow: to restore selected areas of temporal or supraorbital deficiency.
Cheeks and midface: to restore contour in specific deep or superficial fat compartments, and improve the nasolabial fold and the lid-cheek junction.
Lower eyelid and tear trough: particularly when there is true volume deficiency, as an adjunct to lower blepharoplasty and fat transposition, or when a safer alternative to hyaluronic acid is needed after dissolving.
Chin and jawline transitions: for chin fat pad atrophy, pre-jowl sulcus and to improve facial proportions.
Perioral region: conservative grafting where loss of soft-tissue volume contributes to contour changes and small wrinkles (SNIF).
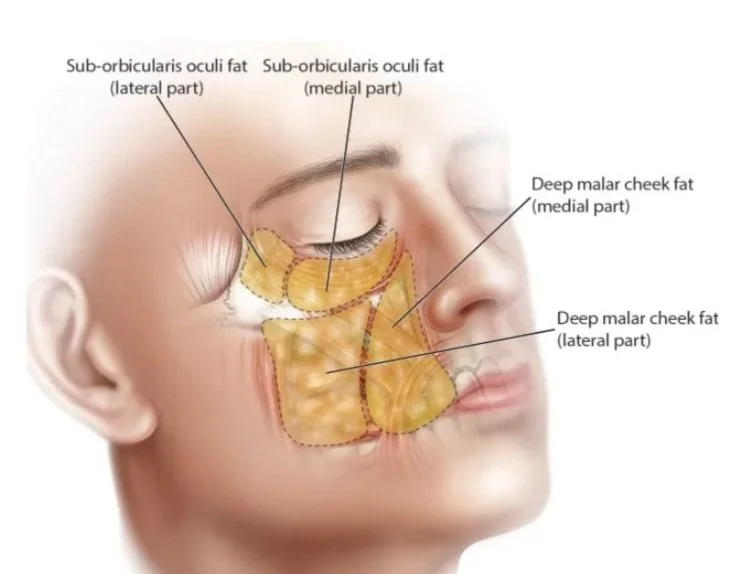
Deep fat pads are mostly the ones who lose volume with time. They should be injected very strategically. (Reproduced from Rohrich, R. Pessa, J. The Fat Compartments of the Face: Anatomy and Clinical Implications for Cosmetic Surgery. Plast. Reconstr. Surg. 119: 2219, 2007.)
How is facial fat grafting performed?
Fat is harvested through a small liposuction cannula, usually from the abdomen or thighs.
It is then processed before being transferred into small syringes
After local anesthesia, it is carefully injected into the planned facial compartments and tissue planes.
Different fat preparations and particle sizes can be used depending on the area being treated. Microfat grafts are particularly useful in delicate areas such as the eyelids, while larger structural parcels may be appropriate in deeper facial compartments. Nanofat (Stem cells and growth factors that come with the fat cells) can be injected or microneedled in the same setting.
Facial fat grafting can be performed alone or combined with procedures such as facelift, blepharoplasty, brow lift or lip lift.
What is the recovery after facial fat grafting like?
No sutures or scars on the face.
Minimal pain with medication.
Swelling and bruising are minimal but expected during the first several days and are usually most noticeable during the first week. Many patients are socially comfortable within approximately 1–2 weeks, although subtle swelling, particularly around the eyelids, can persist longer.
The initial appearance should not be interpreted as the final volume. Some of the early fullness is swelling, and a proportion of the transferred fat will be resorbed during the following months. I generally reassess the longer-term contour once the graft has had time to settle.
1st Follow-up: 7 days
2nd Follow-up: 3 months to evaluate graft take.
Can usually be combined with a facelift, lip lift, brow lift, or blepharoplasty.
-
Facial fat grafting restores volume lost with aging.
Common areas include the midface, temples, jawline transitions, and periorbital region. The goal is not enlargement, but structural balance, softening shadows and re-establishing continuity between facial units.
Volume should restore proportion. I cannot perform a facelift with fat grafting.
-
Transferred fat that survives becomes living tissue. However, not all injected fat survives (around 70% does).
A percentage of resorption is expected in the early months. Long-term stability depends on technique, recipient site vascularity, and patient-specific factors. Subtle refinement may occasionally be required.
It is not a temporary filler, but it is also not entirely predictable at the millimeter level.
-
It should not.
Overcorrection or poor placement can create heaviness. Conservative layering and anatomical respect are essential. Volume is distributed in planes that restore youthful contours rather than simply adding bulk.
The objective is contour, not fullness.
-
Fat grafting uses your own tissue and is typically performed in a surgical setting. It allows for broader structural contour correction rather than focal volumization.
Fillers are useful for precise, small-volume adjustments. Fat grafting is more appropriate when generalized deflation or multi-area correction is present.
They are tools and not competitors.